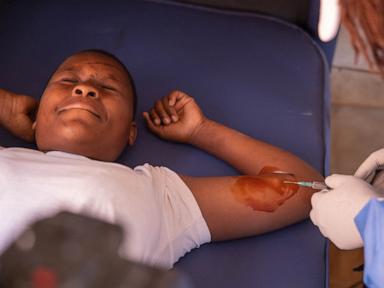
Sub-Saharan Africa accounts for seventy percent of global maternal deaths, recording approximately 180,000 pregnancy-related fatalities annually. Within this demographic friction zone, adolescent girls face compounding barriers to reproductive health access that threaten to reverse decades of public health gains. The erosion of this infrastructure is not a random humanitarian crisis; it is the predictable output of a systemic failure driven by three intersecting vectors: institutional funding contraction, macroeconomic shipping disruptions, and entrenched socio-cultural friction. Deconstructing these variables exposes the fragility of current reproductive health delivery models across the continent.
The Macroeconomic Shock of Aid Contraction
Public health delivery systems in developing economies rely heavily on external donor financing. Recent shifts in foreign assistance allocations have created an immediate fiscal deficit. For instance, the dismantling of major United States aid programs abruptly terminated multi-year grants supporting reproductive healthcare delivery, stranding millions of dollars in unspent capital and instantly halting mobile clinic operations.
When bilateral donors abruptly withdraw, recipient nations experience a severe capital shock. Local non-governmental organizations that bridge the gap between municipal clinics and remote settlements find their operational budgets decimated. While domestic actors attempt to absorb the shortfall—such as Zimbabwe's Ministry of Health allocating localized procurement funds—public treasuries lack the liquidity to replace multi-million-dollar international funding streams. This creates an immediate resource rationing environment where adolescent health programs are routinely deprioritized in favor of acute emergency care.
Global Supply Chain Vulnerabilities and Geopolitical Friction
Beyond direct financial grants, physical access to contraceptives depends on stable, international maritime and overland supply chains. Geopolitical conflicts far from the African continent exert direct pressure on local availability. Ongoing disruptions and security crises involving maritime choke points near the Middle East—specifically tied to regional conflicts such as the Iran war—have severely impacted shipping logistics, freight timelines, and medical manufacturing inputs.
When container shipping routes face increased insurance premiums, naval threats, or physical blockages, the cost of delivering pharmaceutical commodities escalates. Essential reproductive items, including long-acting reversible contraceptives like implants and intrauterine devices, experience acute bottlenecks at ports of entry. By the time supplies clear customs and reach decentralized rural clinics, stockouts have already occurred. The distance between manufacturing hubs and end-users becomes a critical point of failure when global trade networks contract.
Institutional Stigma and Regulatory Friction
Physical availability alone does not equate to utilization. The micro-level environment is defined by severe regulatory and cultural friction. In many jurisdictions, restrictive parental consent laws create an impossible bureaucratic threshold for minors. Requiring explicit parental approval for contraceptive access ignores the social reality of adolescent populations, driving young people entirely out of the formal healthcare architecture.
This institutional barrier is reinforced by community-level stigma. Healthcare facilities are frequently staffed by personnel embedded within the local social fabric, turning clinics into sites of surveillance rather than care. Adolescents seeking reproductive guidance face moral judgment, gossip, and the threat of exposure to family or religious networks.
To bypass this scrutiny, vulnerable populations rely on low-profile, decentralized mechanisms—such as mobile health caravans tucked into discrete urban fringes. However, these discreet lifelines are precisely the first to fold when international grants evaporate and localized operating costs become unsustainable. The resulting vacuum leaves adolescents with two alternatives: complete abstinence without education, or reliance on unregulated, highly dangerous underground abortion methods that drive maternal mortality statistics higher.
Strategic Reconfiguration of Delivery Networks
Mitigating the collapse of adolescent reproductive health access requires moving away from donor-dependent, centralized models toward resilient, localized frameworks. Public health planners must decouple supply chains from geopolitical volatility by regionalizing manufacturing partnerships within the African continent. Concurrently, regulatory frameworks must be systematically reformed to decouple adolescent healthcare access from mandatory parental consent, eliminating the legal friction that forces vulnerable populations into secrecy. Funding mechanisms must transition from fragile, short-term foreign aid grants to sustainable domestic health insurance integration, ensuring that contraceptive availability is treated as a baseline economic infrastructure rather than a discretionary humanitarian project.
Fubu Toy review
This video provides a documentary look at the operational realities and on-the-ground mobile health initiatives affected by these funding and supply chain constraints in Southern Africa.


